A scale cannot distinguish fat loss from changes in muscle, other lean tissue, or water. A body-composition substudy within SURMOUNT-1 helps fill that gap: among 160 participants with paired scans, tirzepatide produced substantially greater reductions in fat mass and lean mass than placebo over 72 weeks. Roughly three-quarters of the weight lost was fat and one-quarter was lean tissue. That does not mean participants lost one-quarter of their starting muscle.
The distinction matters for ongoing care. A favorable average shift in body composition does not establish that every person retained strength, avoided functional problems, or needs the same monitoring. This analysis draws on the full published body-composition report and its publisher correction, the indexed primary-report abstracts for SURMOUNT-1 and STEP-HFpEF, and FDA material on compounded drugs. Together, they clarify what was measured, where uncertainty remains, and why responsibility for interpreting changes should remain clear across care handoffs.
At a glance
- Paired-scan population
- The analysis included 160 participants: 124 receiving pooled tirzepatide doses and 36 receiving placebo; approximately 73% were female.Sources: [1]
- Fat mass
- At 72 weeks, fat mass declined 33.9% from baseline with tirzepatide versus 8.2% with placebo.Sources: [1]
- Lean mass
- Lean mass declined 10.9% from baseline with tirzepatide versus 2.6% with placebo. DXA lean mass is not a direct measurement of skeletal muscle or strength.Sources: [1]
- The 75/25 denominator
- Approximately 75% of lost weight was fat and 25% was lean mass in both groups—not 25% of starting muscle.Sources: [1]
- Corrected figure units
- An August 2025 correction changed Figure 4’s fat- and lean-mass axis units to kilograms, not percent; the abstract’s percentage changes were not corrected.Sources: [3]
A body-composition question inside a larger randomized trial
SURMOUNT-1 enrolled 2,539 adults without diabetes who had a body mass index of at least 30, or at least 27 with a weight-related complication. Participants were randomly assigned to once-weekly subcutaneous tirzepatide at 5, 10, or 15 mg, or placebo, for 72 weeks. These doses identify research arms, not treatment instructions. Both groups received lifestyle counseling, so the comparison was medication plus counseling versus placebo plus counseling.
The parent trial’s coprimary endpoints were percentage weight change and the proportion losing at least 5% of starting weight. The substudy asked a different question: whether the three tirzepatide groups, pooled together, had a greater percentage reduction in fat mass than placebo. Lean-mass changes were key secondary endpoints; several other analyses were exploratory.
Pooling strengthened the overall comparison but made this primarily a combined-treatment analysis, not a definitive comparison of body composition at each dose. As the guide to interpreting clinical trials explains, the endpoint and population determine what a study can answer. Here, the principal question concerned fat mass—not strength, disability, or a clinical diagnosis of muscle loss.
Who contributed scans—and who did not
Although 255 people enrolled in the DXA substudy, 160 contributed the paired measurements used in the analysis. That is approximately 63% of substudy enrollees and 6% of the parent trial. The analysis included 124 tirzepatide recipients and 36 placebo recipients. Their mean age was 46.2 years, mean weight 102.5 kg, and mean BMI 38.0; 73.1% were female and 75.6% were White.
Participants came from 28 sites with suitable scanners across several countries and territories. Scanner size and weight limits, as well as implants or other factors interfering with accurate imaging, could exclude people from scanning. Consequently, randomization in the parent trial does not erase the selection involved in entering the substudy and contributing usable paired scans.
The report used baseline and week-72 or early-discontinuation scans, with three missing week-72 values carried forward from an earlier observation. This approach preserves some data but assumes the earlier measurement can represent a later endpoint. The result is informative for this analyzed group; it is less certain how closely it describes people who lacked follow-up imaging or populations sparsely represented.
STUDY DATA · GLP-1 Treatment Desk
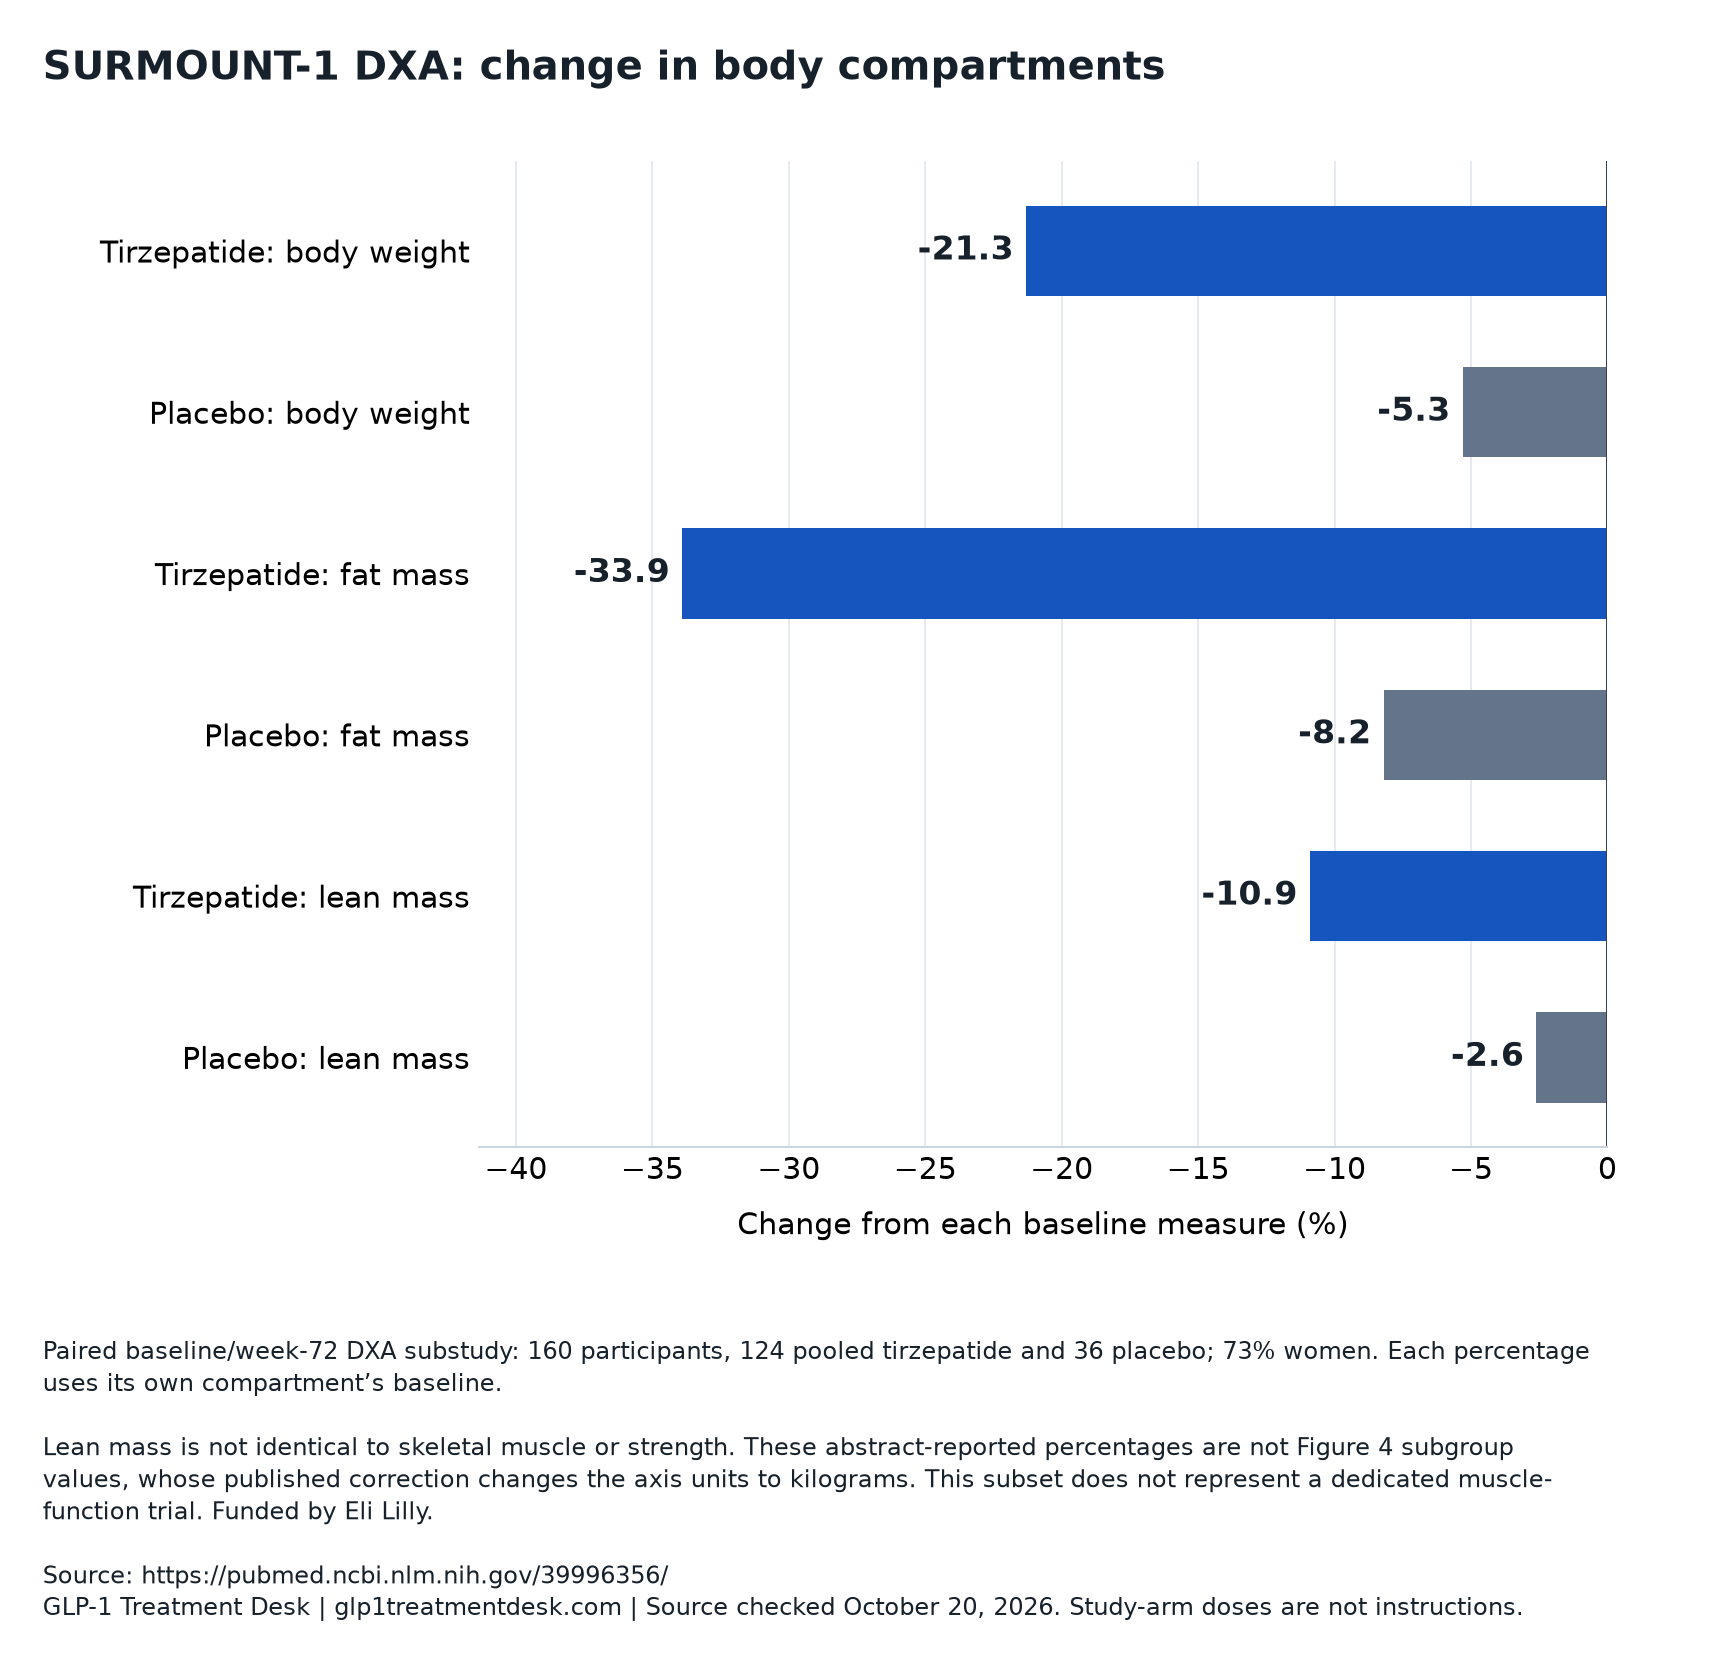
SURMOUNT-1 DXA: change in body compartments
Paired baseline/week-72 DXA substudy: 160 participants, 124 pooled tirzepatide and 36 placebo; 73% women. Each percentage uses its own compartment’s baseline.
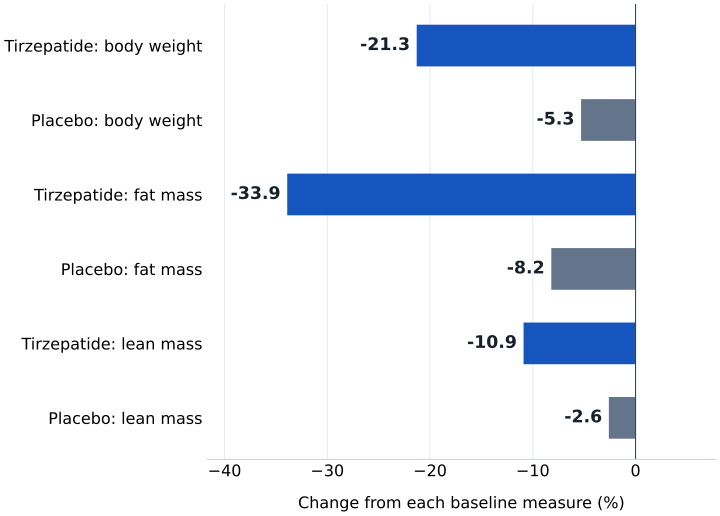
| Study group | Change from each baseline measure (%) |
|---|---|
| Tirzepatide: body weight | -21.3 |
| Placebo: body weight | -5.3 |
| Tirzepatide: fat mass | -33.9 |
| Placebo: fat mass | -8.2 |
| Tirzepatide: lean mass | -10.9 |
| Placebo: lean mass | -2.6 |
Lean mass is not identical to skeletal muscle or strength. These abstract-reported percentages are not Figure 4 subgroup values, whose published correction changes the axis units to kilograms. This subset does not represent a dedicated muscle-function trial. Funded by Eli Lilly.
Original visualization of published aggregate data. No individual prediction or provider performance is represented. Original research ↗
What a DXA lean-mass measurement actually contains
Dual-energy X-ray absorptiometry, or DXA, estimates body compartments using X-rays at two energy levels. In this report, lean mass meant nonfat tissue excluding bone mineral content. It includes skeletal muscle but also water, organs, and other soft tissues. Fat-free mass is a different term because it includes bone mineral; the investigators did not evaluate that compartment as an endpoint.
Sites were instructed to use the same scanner and software for each participant, with similar positioning, hydration, and time of day. A blinded central reader evaluated scans. These procedures reduce measurement variability, but they do not turn lean mass into a muscle-specific measurement or separate changes in tissue protein from changes in water.
The clinically important distinction is between quantity and performance. A DXA result describes estimated tissue mass; it does not show how much force a person can generate, how easily they rise from a chair, or whether everyday tasks became harder. Those outcomes require separate assessment. The study therefore cannot diagnose functional impairment from the lean-mass percentage alone.
| Measure | What it describes | What it cannot establish alone |
|---|---|---|
| Body weight | Total mass measured on a scale | Which tissues account for the change |
| DXA lean mass | Estimated nonfat soft tissue, excluding bone mineral | Skeletal muscle loss specifically or muscle strength |
| Physical function | Ability or perceived ability to perform activities | The amount or composition of tissue responsible |
Reading the percentage changes without mixing denominators
At 72 weeks, estimated mean body-weight change was −21.3% with pooled tirzepatide versus −5.3% with placebo. Fat-mass change was −33.9% versus −8.2%, and lean-mass change was −10.9% versus −2.6%. Each percentage uses its own starting compartment: starting body weight, starting fat mass, or starting lean mass. The fat and lean percentages therefore should not be added to reconstruct percentage weight loss.
The between-group fat-mass difference was −25.7 percentage points, with a 95% confidence interval from −31.4 to −20.0. For lean mass, the difference was −8.3 percentage points, with a confidence interval from −10.6 to −6.1. These intervals describe uncertainty around estimated average treatment differences, not the range of changes experienced by individual participants.
Absolute changes provide another perspective: fat mass declined by 15.9 kg with tirzepatide versus 3.6 kg with placebo, while lean mass declined by 5.6 versus 1.2 kg. The between-group differences were −12.3 kg for fat mass, with a 95% confidence interval of −15.1 to −9.6, and −4.4 kg for lean mass, with an interval of −5.6 to −3.2.
| Measure | Pooled tirzepatide | Placebo |
|---|---|---|
| Body weight | −21.3% | −5.3% |
| Fat mass | −33.9% | −8.2% |
| Lean mass | −10.9% | −2.6% |
| Absolute fat mass | −15.9 kg | −3.6 kg |
| Absolute lean mass | −5.6 kg | −1.2 kg |
Why one-quarter of lost weight is not one-quarter of muscle
The investigators calculated the fat-loss share as fat mass lost divided by fat plus lean mass lost. The corresponding lean-loss share used lean mass lost as the numerator. In the detailed results, these shares were 74% fat and 26% lean with tirzepatide, compared with 75% and 25% with placebo. The abstract reasonably summarized both as approximately 75/25.
For a hypothetical 10 kg reduction divided into those two compartments, a 75/25 split would mean 7.5 kg of fat and 2.5 kg of lean tissue. It would not mean losing 25% of the person’s starting lean tissue, much less 25% of starting skeletal muscle. The actual tirzepatide group’s lean-mass change from its own baseline was 10.9%.
A similar proportion also does not mean a similar absolute loss. When total weight loss is much larger, the same one-quarter share represents more kilograms. Interpretation: the placebo comparison argues against a dramatically different average partition of lost tissue, but it does not make the larger absolute lean-tissue reduction irrelevant. Both the share and the amount matter when considering an individual’s history and function.
The correction changes how Figure 4 must be read
The publisher issued a correction on August 20, 2025: Figure 4’s fat- and lean-mass y-axis units should be kilograms, not percent. That figure groups tirzepatide recipients by how much weight they lost. Reading its values as percentages would confuse absolute tissue losses with changes relative to starting tissue mass.
The correction did not revise the abstract’s percentage changes. The comparison table above therefore uses the reported baseline-relative percentages, clearly separated from kilogram changes. A corrected axis is not evidence that all findings were overturned, but neither is it a cosmetic detail: units determine the scientific meaning of a plotted number.
Participants with greater weight reductions lost more fat and more lean mass in absolute terms. However, the weight-loss groups were formed after outcomes occurred, rather than randomly assigned. They cannot establish that aiming for a particular amount of loss causes a particular tissue distribution, or that one weight-loss category is inherently better for muscle preservation.
Fat distribution improved, but subgroup precision was limited
Beyond total fat, the investigators reported a 40.1% decline in estimated visceral fat with tirzepatide versus 7.3% with placebo. The difference was −32.8 percentage points, with a 95% confidence interval from −42.8 to −22.8. Waist circumference fell 18.1 cm versus 3.4 cm, a difference of −14.7 cm, with an interval from −18.5 to −11.0.
Visceral fat was estimated from the abdominal region using scanner-manufacturer algorithms, not directly measured by computed tomography. These findings support a change in fat distribution, but this substudy did not establish how much that change independently affected disease outcomes. A large imaging change and a demonstrated clinical benefit are different kinds of evidence.
Post hoc analyses explored age, sex, and weight-loss categories. Most showed broadly similar fat-versus-lean proportions, but some placebo subgroups contained very few participants. There was no adjustment for multiple statistical comparisons. The findings are useful for generating questions, not proving that older adults or either sex have identical responses. In particular, averages cannot settle concerns in people with preexisting weakness or low muscle reserves.
Better function and less lean tissue can coexist
The body-composition article cites improved patient-reported physical function in the broader SURMOUNT-1 population. That is relevant but does not replace direct strength or performance testing in the paired-scan group. Less body weight to move could plausibly make activities easier despite less lean tissue; this is an interpretation, not a mechanism demonstrated by the substudy.
A separate example shows why function needs its own endpoint. In STEP-HFpEF, 529 people with obesity and heart failure with preserved ejection fraction received once-weekly semaglutide 2.4 mg or placebo for 52 weeks. Symptom and physical-limitation scores improved by an additional 7.8 points, with a 95% confidence interval of 4.8 to 10.9. Six-minute walking distance improved by an additional 20.3 meters, with an interval of 8.6 to 32.1.
The STEP-HFpEF analysis concerns a different drug, population, and measurement strategy; it does not prove strength preservation with tirzepatide. Likewise, SURMOUNT-4’s withdrawal design addresses maintenance rather than the tissue composition measured here. These studies answer complementary questions, not interchangeable ones.
Tolerability and analysis choices belong beside the scan results
In the parent SURMOUNT-1 report, gastrointestinal adverse events were most common, generally mild to moderate, and concentrated during dose escalation. Adverse events led to treatment discontinuation in 4.3%, 7.1%, and 6.2% of the 5-, 10-, and 15-mg groups, respectively, versus 2.6% with placebo. Those are parent-trial findings, not adverse-event rates calculated specifically for the 160-person scan analysis.
The parent report estimated weight changes regardless of treatment discontinuation: −15.0%, −19.5%, and −20.9% across tirzepatide doses versus −3.1% with placebo. Those figures differ from the pooled substudy result because the populations and analysis approaches differ. They should not be treated as contradictory estimates of one identical quantity.
Eli Lilly funded the body-composition work and participated in design, data collection, analysis, interpretation, and reporting. Several authors were company employees and shareholders. The randomized design and blinded scan reading remain strengths, but independent replication would be valuable. The study also did not analyze nutrient intake or activity in relation to DXA changes, so it cannot identify a proven muscle-preservation regimen.
Continuity means someone interprets the whole picture
Interpretation for care continuity: these findings make clinical history and changes in daily functioning relevant alongside scale weight. They do not establish that everyone needs DXA or a particular testing schedule. Useful organizational questions concern who receives reports, who evaluates new difficulties, and who retains the treatment history when a platform or clinician changes. The care-journey guide separates those responsibilities.
A billing or delivery arrangement is not itself evidence of clinical follow-up. The guide to changing programs discusses clarifying responsibility during transitions. For a named service, the Mochi Health review can be used to check documentary terms about care and handoffs—not to infer access to the studied product, body-composition expertise, or trial-like outcomes.
Product identity also limits transferability. FDA states that compounded drugs are not approved or reviewed before marketing for safety, effectiveness, or quality, and identifies concerns including dosing errors and semaglutide salt ingredients. The formulation-check guide helps frame product and route questions. Results from this injectable tirzepatide trial do not establish equivalence for compounded preparations, oral products, other formulations, or any provider’s service.
Questions & answers
Does the study show that tirzepatide causes muscle wasting?
It shows a reduction in DXA lean mass, which includes muscle but also water, organs, and other soft tissues. It did not directly measure muscle-specific loss, strength, or a muscle-wasting diagnosis. Calling the entire lean-mass reduction muscle wasting goes beyond the measurements; dismissing it as meaningless would also go beyond the evidence.
How can fat mass fall 33.9% while weight falls 21.3%?
The denominators differ. The 33.9% figure describes the fraction of starting fat mass lost, while 21.3% describes the fraction of starting total body weight lost. Because fat is only one part of body weight, a larger percentage reduction in that compartment can coexist with a smaller percentage reduction overall.
Did the study establish a way to prevent lean-mass loss?
No. Participants received lifestyle counseling, but there was no specific strength-training protocol, and the analysis did not connect measured nutrient intake or activity with tissue changes. It therefore cannot establish a protein target, exercise prescription, or other regimen that reliably preserves lean mass during treatment.
Can these findings determine whether someone needs a DXA scan?
Not by themselves. This was a research substudy, not a trial comparing monitoring strategies. It did not show that routine scanning improves outcomes or establish a testing interval. Its main contribution is to explain average tissue changes and the limits of interpreting scale weight or lean mass in isolation.
What remains unanswered after 72 weeks?
Important questions include longer-term tissue trajectories, direct strength and performance outcomes, and responses among people with low baseline muscle reserves. The study also cannot determine what happens to each body compartment after treatment withdrawal. Its relatively small, predominantly female paired-scan population limits precise conclusions about less-represented groups.
Our assessment
The strongest conclusion is specific: in the analyzed SURMOUNT-1 subgroup, tirzepatide produced substantially greater fat loss and greater lean-tissue loss than placebo, with broadly similar proportions of lost weight coming from each compartment. That supports a predominantly fat-loss interpretation, not a claim of muscle preservation or functional harm. For continuity of care, the editorial implication is to keep product identity, treatment history, tolerability, and functional concerns connected to an identifiable clinical decision-maker. Neither a scale nor a scan can replace that broader interpretation.
Sources & documentation
Scientific and official sources consulted October 20, 2026. Study findings apply to the populations, products and time periods described; they are not provider outcome data.
- Body composition changes during weight reduction with tirzepatide in the SURMOUNT-1 study of adults with obesity or overweight. ↗
- Tirzepatide Once Weekly for the Treatment of Obesity. ↗
- Correction to "Body composition changes during weight reduction with tirzepatide in the SURMOUNT-1 study of adults with obesity or overweight". ↗
- Semaglutide in Patients with Heart Failure with Preserved Ejection Fraction and Obesity. ↗
- FDA concerns about unapproved GLP-1 drugs ↗