ATTAIN-1 tested a practical scientific question: how much additional weight reduction would once-daily oral orforglipron produce over 72 weeks when compared with placebo, with both groups receiving lifestyle support? Among 3,127 randomized adults without diabetes, the highest study-dose group averaged an 11.2% reduction in body weight, versus 2.1% with placebo. The result establishes a treatment effect within a defined research pathway—not a promised outcome for every person or every service arranging care.
Understanding that pathway requires separating enrollment criteria, treatment assignment, continued observation, and statistical estimation. It also requires separating historical research terminology from current regulation: Foundayo, the marketed orforglipron tablet, received initial US approval in 2026. This analysis uses the indexed primary report abstracts and available official labeling and FDA material; it does not represent examination of every trial protocol, supplement, or full research article.
At a glance
- Design
- ATTAIN-1 randomized 3,127 adults without diabetes in a multinational, double-blind, placebo-controlled phase 3 trial lasting 72 weeks.Sources: [1]
- Primary result
- Mean weight change was −11.2% (95% CI, −12.0 to −10.4) with the highest investigational study dose, versus −2.1% (95% CI, −2.8 to −1.4) with placebo.Sources: [1]
- Outcome framework
- The primary analysis used a treatment-regimen estimand in the intention-to-treat population, rather than restricting the question to uninterrupted treatment.Sources: [1]
- Treatment discontinuation
- Adverse events led to treatment discontinuation in 5.3%–10.3% of orforglipron participants across study groups, compared with 2.7% receiving placebo.Sources: [1]
- Current product distinction
- Foundayo is US-approved, but ATTAIN-1's investigational milligram doses are not current marketed tablet strengths and are not interchangeable milligram for milligram.Sources: [2]
Enrollment defined the population behind the average
The indexed ATTAIN-1 abstract describes participants as adults with obesity without diabetes. The official label provides more detailed eligibility: adults with a body mass index, or BMI, of at least 30, or BMI of 27 to below 30 plus at least one weight-related condition. Examples included hypertension, abnormal blood lipids, obstructive sleep apnea, and cardiovascular disease. Type 2 diabetes was excluded. BMI relates weight to height; it is an enrollment measure, not a complete description of health.
The label identifies a mean starting weight of 103.2 kilograms and mean BMI of 37. Participants averaged 45 years of age, with an age range of 18–88; 64% were female. Hypertension affected 40%, and dyslipidemia affected 39%. These characteristics give the results context: the average came from a population with substantial excess weight and common associated conditions, rather than from adults seeking a small cosmetic weight change.
Eligibility is only the first step in research. Random assignment occurs after entry criteria are applied, while ordinary clinical care involves individualized assessment without experimental assignment. Our care-journey guide separates those service responsibilities. The trial does not establish that a particular online intake process identifies the same population or reproduces its observation.
Randomization isolated the drug contribution
Participants were assigned in a 3:3:3:4 ratio to once-daily oral orforglipron at investigational doses of 6, 12, or 36 milligrams, or to placebo. The ratio allocated more participants to the shared placebo group than to any single active group. Randomization reduces systematic differences between groups, making the assigned intervention a stronger explanation for later differences than it would be in an uncontrolled before-and-after comparison.
Double-blinding means treatment assignment was concealed from participants and investigators. Both active and placebo groups also received lifestyle intervention. The label describes reduced-calorie diet instruction and physical activity counseling beginning with study medication and continuing throughout follow-up. Thus, the comparison estimates the added effect of assigned drug treatment within that shared setting; it does not compare medication plus support against no care.
ATTAIN-1 was funded by Eli Lilly and registered as NCT05869903. Sponsorship is relevant context, but the central scientific strengths remain the randomized comparator, prespecified primary measurement, and substantial sample. The accessible abstract does not describe every contact, adherence assessment, or escalation detail, so a precise visit-by-visit care schedule cannot be reconstructed from it.
STUDY DATA · GLP-1 Treatment Desk
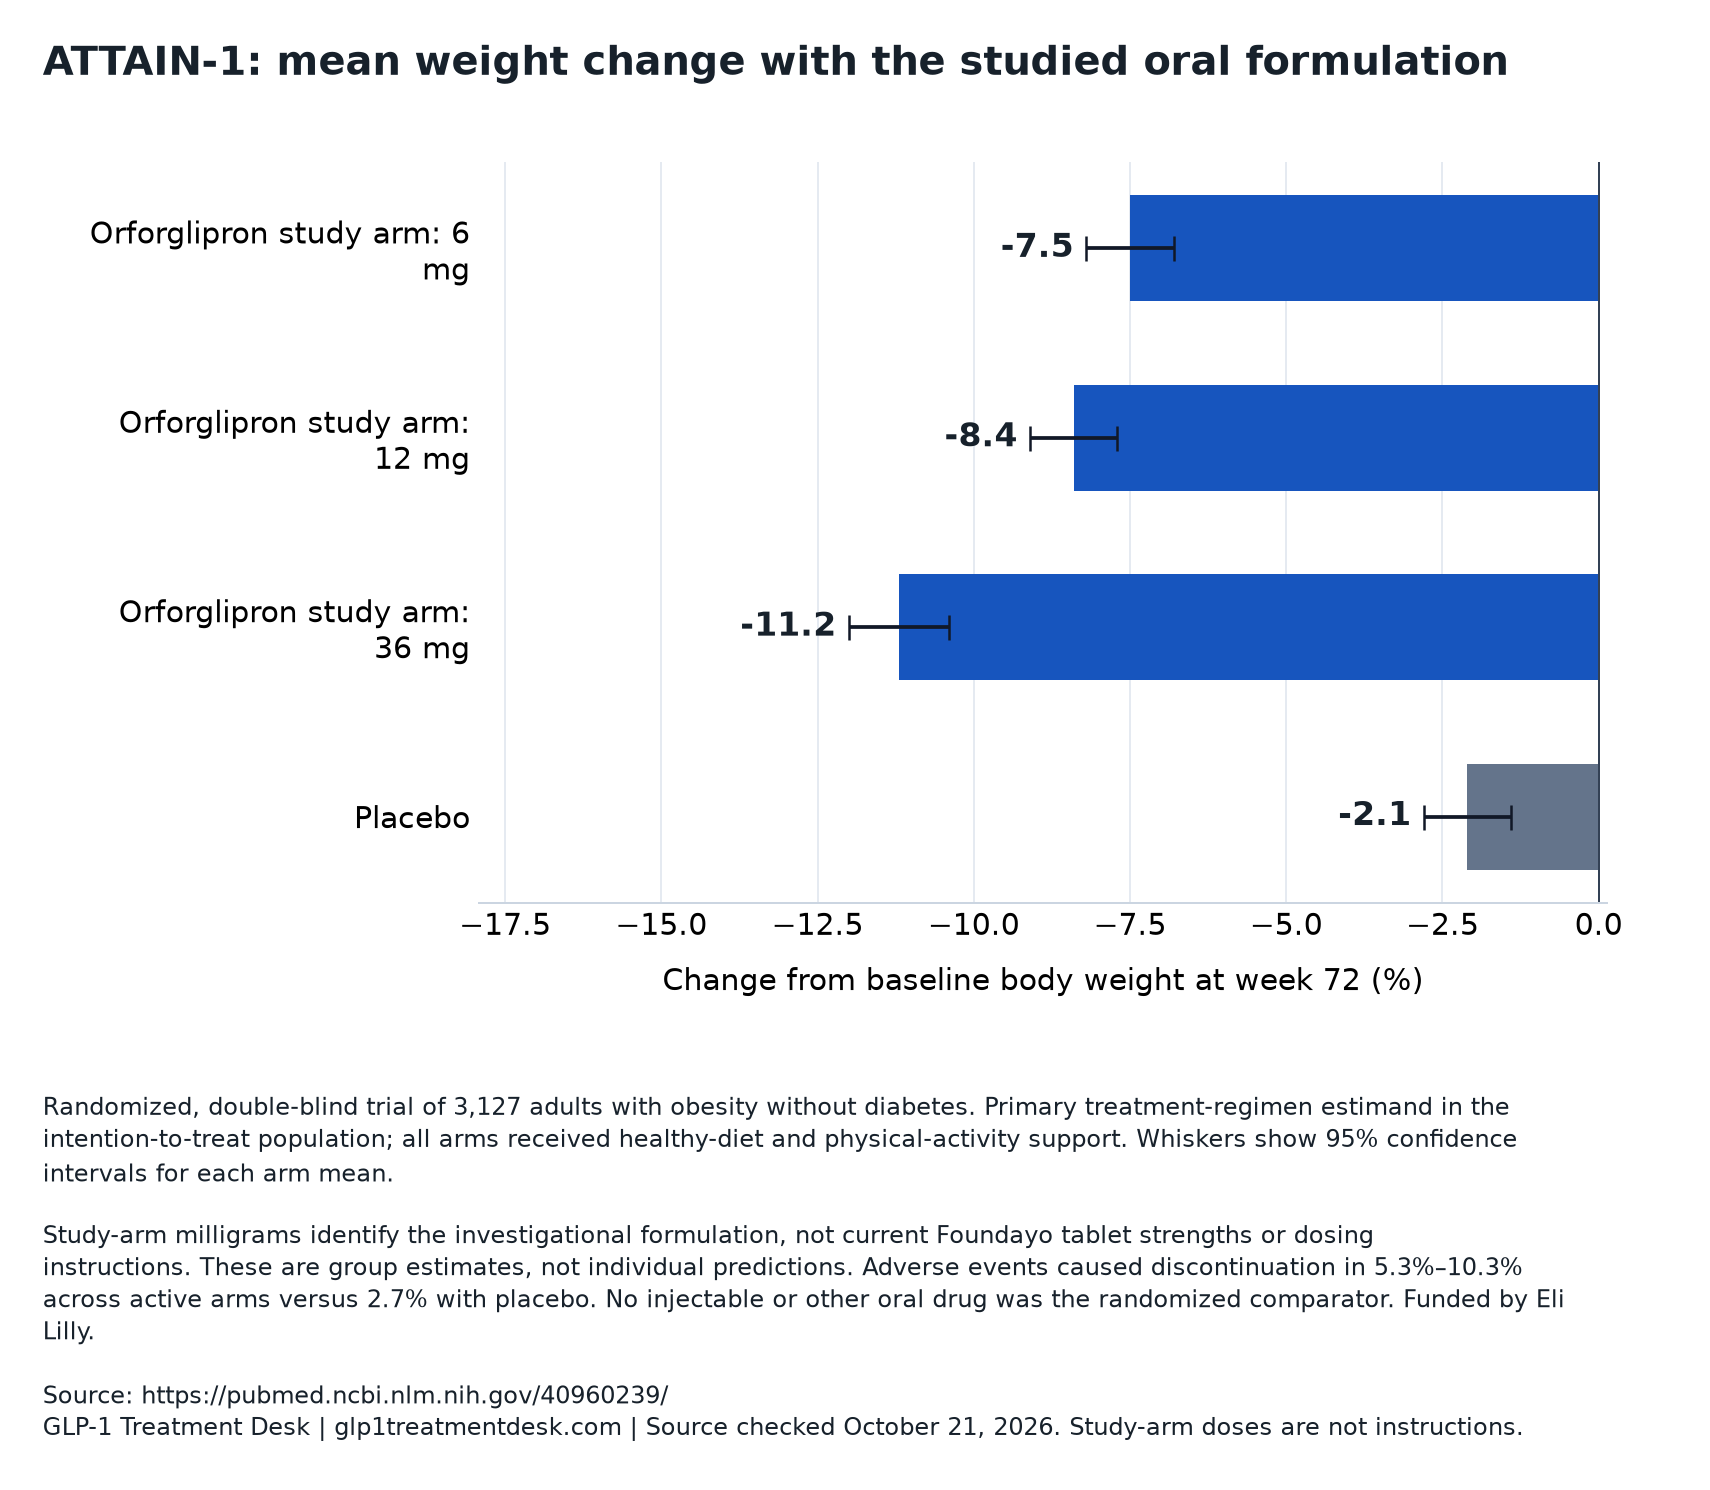
ATTAIN-1: mean weight change with the studied oral formulation
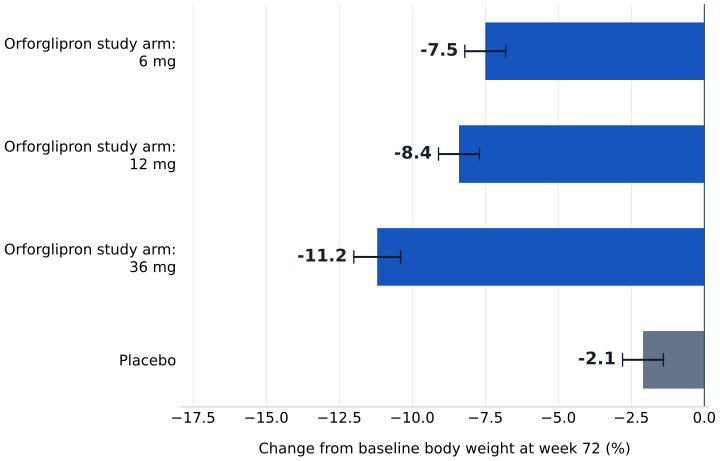
Randomized, double-blind trial of 3,127 adults with obesity without diabetes. Primary treatment-regimen estimand in the intention-to-treat population; all arms received healthy-diet and physical-activity support. Whiskers show 95% confidence intervals for each arm mean.
| Study group | Change from baseline body weight at week 72 (%) |
|---|---|
| Orforglipron study arm: 6 mg | -7.5 |
| Orforglipron study arm: 12 mg | -8.4 |
| Orforglipron study arm: 36 mg | -11.2 |
| Placebo | -2.1 |
Study-arm milligrams identify the investigational formulation, not current Foundayo tablet strengths or dosing instructions. These are group estimates, not individual predictions. Adverse events caused discontinuation in 5.3%–10.3% across active arms versus 2.7% with placebo. No injectable or other oral drug was the randomized comparator. Funded by Eli Lilly.
Original visualization of published aggregate data. No individual prediction or provider performance is represented. Original research ↗
The primary analysis counted assignment, not just persistence
The primary endpoint was percentage change in body weight from baseline to week 72. The analysis used the intention-to-treat population—all randomized participants—and a treatment-regimen estimand. An estimand defines the treatment question being answered. Here, the focus was the effect of assignment to the regimen, rather than only the outcome under uninterrupted adherence.
That distinction matters because discontinuation was not rare. In the label's account of Trial 1, approximately 22%–24% of active-treatment participants discontinued trial drug, compared with 30% receiving placebo. These are all-cause treatment-discontinuation figures, not adverse-event discontinuation rates, and they do not mean that everyone who stopped medication also stopped contributing outcome information.
Some week-72 weights nevertheless were missing: 14%–16% across active groups and 24% with placebo. The label describes multiple imputation, a method that fills missing values using several statistically constructed datasets and combines the analyses. It used information from the same randomized group, distinguishing missingness potentially related to treatment from other missingness. This preserves a broader assignment-based question, but the result still depends on assumptions about unobserved weights.
Reading the weight changes without inflating them
All three investigational groups had greater average weight reduction than placebo. The primary abstract reports reductions of 7.5%, 8.4%, and 11.2%, compared with 2.1%. Subtracting the placebo change gives additional reductions of 5.4, 6.3, and 9.1 percentage points. These calculated contrasts describe differences in average percentage weight change; they are not relative risk reductions.
For a hypothetical starting weight of 100 kilograms, an 11.2% reduction corresponds to 11.2 kilograms, while 2.1% corresponds to 2.1 kilograms. The arithmetic illustrates the scale, not an individual prediction. The 95% confidence interval around the highest group's mean concerns uncertainty in the estimated group average. It does not mean that 95% of participants lost between 10.4% and 12.0%.
The label reports slightly different Trial 1 estimates—11.1% at the highest equivalent marketed dosage and 2.1% with placebo. They should remain identified with their respective reports rather than silently combined. The headline here is the primary abstract's 11.2% treatment-regimen result, not a larger figure from a different efficacy question.
| Assigned investigational arm | Mean change (95% CI) | Additional reduction versus placebo, calculated |
|---|---|---|
| Orforglipron 6 mg | −7.5% (−8.2 to −6.8) | 5.4 percentage points |
| Orforglipron 12 mg | −8.4% (−9.1 to −7.7) | 6.3 percentage points |
| Orforglipron 36 mg | −11.2% (−12.0 to −10.4) | 9.1 percentage points |
| Placebo | −2.1% (−2.8 to −1.4) | Reference |
Response thresholds reveal variation the mean hides
In the highest investigational-dose group, 54.6% reached at least 10% weight reduction, 36.0% reached at least 15%, and 18.4% reached at least 20%. The corresponding placebo proportions were 12.9%, 5.9%, and 2.8%. These thresholds show that a mean around 11% coexisted with both larger and smaller responses.
The categories overlap. Someone losing 20% also meets the 15% and 10% thresholds, so adding the three percentages would count some people repeatedly. Conversely, 45.4% of the highest-dose group did not reach 10%. That remainder is not equivalent to treatment failure: it includes a range of smaller reductions and potentially other weight trajectories.
Calculated absolute differences were 41.7 percentage points for reaching 10%, 30.1 points for reaching 15%, and 15.6 points for reaching 20%. These describe differences in the proportion meeting each endpoint, not additional percentage weight loss. Distinguishing those two uses of percentages prevents a common misreading of responder results.
Improvements beyond weight were measurements, not event prevention
The abstract reports improvements versus placebo in waist circumference, systolic blood pressure, triglycerides, and non-HDL cholesterol. Non-HDL cholesterol captures cholesterol carried outside high-density lipoprotein particles. These measurements help characterize physiological changes accompanying treatment, but they do not establish how many heart attacks, strokes, or other clinical events were prevented.
The label gives scale to selected findings. In Trial 1's highest equivalent marketed-dosage group, waist circumference declined by 10 centimeters versus 3.1 centimeters with placebo; the adjusted difference was −6.9 centimeters, with a 95% confidence interval of −7.8 to −6.0. Systolic blood pressure showed an adjusted difference of −4.9 mm Hg, with a 95% interval of −6.1 to −3.8.
The label marks the blood-pressure comparison as not controlled for multiplicity, meaning its statistical interpretation did not receive the same protection against multiple-testing errors as certain confirmatory endpoints. Pulse also increased: the highest group's adjusted difference was 4.1 beats per minute versus placebo. A scientifically useful summary includes that direction of change alongside favorable measurements, rather than describing every cardiometabolic effect as improved.
Tolerability affected whether treatment continued
Gastrointestinal effects were the most common adverse events in ATTAIN-1 and were mostly mild to moderate. Nonetheless, adverse events led 5.3%–10.3% of active-group participants to discontinue treatment, compared with 2.7% receiving placebo. The abstract provides this range across groups without an arm-by-arm breakdown. It also does not say that every adverse-event discontinuation was gastrointestinal.
The official label adds pooled safety information from two weight-management trials, one without diabetes and one with type 2 diabetes. Those pooled figures are not ATTAIN-1-only rates. Gastrointestinal adverse reactions occurred in 60%–69% across active groups versus 37% with placebo. Nausea occurred in 26%–35% versus 10%, and vomiting in 13%–24% versus 4%. Severe gastrointestinal reactions were reported in approximately 3% versus 1%.
The label says nausea, vomiting, and diarrhea were more frequent during escalation and decreased over time. That is an observed population pattern, not assurance that persistent symptoms resolve in a particular person. Scientifically, tolerability and weight response belong in the same assessment because remaining on assigned treatment is part of the pathway producing outcomes. Our follow-up and tolerability guide distinguishes ongoing observation from a one-time prescription encounter.
The label identifies serious risks beyond common stomach symptoms
In the label's pooled trials, acute kidney injury was reported in 0.2% of active-treatment participants versus 0.05% with placebo. Gallstones were reported in 1.0% versus 0.7%, and acute cholecystitis, or gallbladder inflammation, in 0.4% versus 0.3%. Adjudication confirmed six acute pancreatitis events in six treated participants versus two events in one placebo participant. Small event counts limit the precision of comparisons.
The boxed warning requires especially careful wording. Other GLP-1 receptor agonists that are pharmacologically active in rats and mice have produced thyroid C-cell tumors in those species. Orforglipron is not pharmacologically active in rats or mice and was non-carcinogenic at the studied exposures in the label's rodent studies. That finding does not settle human thyroid risk: the human relevance of GLP-1 receptor-dependent rodent findings remains undetermined.
Foundayo is contraindicated with a personal or family history of medullary thyroid carcinoma or multiple endocrine neoplasia syndrome type 2, and with known serious hypersensitivity to its ingredients. Label warnings also address pancreatitis, severe gastrointestinal reactions, dehydration-related kidney injury, gallbladder disease, and other risks. Hypoglycemia was not systematically captured in Trial 1, illustrating that even an apparently reassuring event count must be interpreted alongside how actively the outcome was sought.
Other trials answer different comparison questions
OASIS 4 studied daily oral semaglutide, not orforglipron. Its 307 participants without diabetes were randomized 2:1 to semaglutide or placebo with lifestyle intervention. The study lasted 71 weeks, but its coprimary weight endpoints were assessed at week 64. Mean weight change was −13.6% versus −2.2%, an estimated difference of −11.4 percentage points with a 95% confidence interval of −13.9 to −9.0.
That larger numerical reduction does not establish oral semaglutide's superiority over orforglipron. The drugs were not randomized against each other, and study populations, endpoint timing, observation, and analysis may differ. OASIS 4, funded by Novo Nordisk, also reported gastrointestinal adverse events in 74.0% versus 42.2%. Those percentages should not be used as a direct tolerability ranking against ATTAIN-1.
SURMOUNT-5 demonstrates what an actual head-to-head design looks like: 751 adults were randomized between weekly subcutaneous tirzepatide and semaglutide for 72 weeks. It was open-label and funded by Eli Lilly. Mean changes were −20.2% and −13.7%, respectively, with 95% confidence intervals of −21.4 to −19.1 and −14.9 to −12.6. Neither treatment was oral orforglipron. The SURMOUNT-5 analysis explores that direct comparison; the ESSENCE evidence analysis addresses a different, biopsy-defined research question.
| Trial and population | Assignment and timing | Question directly tested |
|---|---|---|
| ATTAIN-1: 3,127 adults without diabetes | Daily oral orforglipron versus placebo; week 72 | Added weight effect of orforglipron within shared lifestyle support |
| OASIS 4: 307 adults without diabetes | Daily oral semaglutide versus placebo; week-64 endpoints in a 71-week study | Added weight effect of oral semaglutide |
| SURMOUNT-5: 751 adults without type 2 diabetes | Weekly injected tirzepatide versus injected semaglutide; week 72 | Direct comparison of two injectable treatments |
Approved tablets and care services are separate evidence questions
Foundayo's current label establishes that orforglipron is approved for weight reduction and long-term maintenance in eligible adults, alongside diet and activity intervention. It explicitly describes the trials as using an investigational formulation and presents results using equivalent marketed dosages. Therefore, the research doses in the primary abstract identify historical arms; they must not be treated as current tablet strengths or a self-directed conversion scheme.
The distinction extends beyond milligrams. Trial findings do not automatically validate compounded products, another formulation, or a different delivery route. FDA explains that unapproved and compounded GLP-1 products do not undergo its premarket review for safety, effectiveness, and quality. The formulation-check guide separates ingredient name, formulation, route, and dispensing source.
Editorial interpretation: research evidence also does not establish a platform's follow-up performance or contractual continuity. Readers consulting the Ro review or Mochi Health review can use those pages to check documentary terms, not infer access to the studied product or trial-like outcomes. ATTAIN-1 measured neither service contracts nor costs, and its 72-week results do not resolve durability after medication withdrawal or benefits over many years.
Questions & answers
Does 11.2% mean everyone taking orforglipron lost that much?
No. It is an estimated mean for the highest investigational-dose group under the primary treatment-regimen analysis. Individual responses varied substantially: 54.6% reached at least 10% loss, while 18.4% reached at least 20%. The confidence interval describes uncertainty around the group mean, not a likely range for each person.
Why include participants who discontinued treatment?
Keeping participants within their randomized groups preserves the assignment-based comparison and addresses what happens when a treatment regimen is offered, including interruptions or discontinuation. It avoids replacing that question with a selected analysis of persistent users. Missing outcome measurements still require assumptions; the label describes multiple imputation rather than complete observation of every week-72 weight.
Is Foundayo still investigational?
No. The current official label lists initial US approval in 2026. The investigational terminology applies to the formulation used in the trials. Its published study-dose numbers are not current marketed tablet strengths, and the label's presentation of equivalent dosages should not be turned into an individual conversion or dosing plan.
Did ATTAIN-1 prove fewer cardiovascular events?
No. It measured weight change as its primary endpoint and reported changes in waist size, blood pressure, and lipids. Those are clinically relevant measurements, but improvement in a risk marker is not the same outcome as preventing a heart attack, stroke, or cardiovascular death. A dedicated event-based comparison would address a different question.
Does taking a tablet eliminate GLP-1 safety concerns?
No. Oral administration changes the route, not the need to assess adverse effects and contraindications. ATTAIN-1 documented adverse-event discontinuations, and the current label describes common gastrointestinal reactions plus serious warnings. It also identifies drug interactions and potential effects on absorption of other oral medicines. Safety interpretation must remain product-specific rather than assuming that a pill is inherently low-risk.
Our assessment
ATTAIN-1 provides strong randomized evidence that assigned daily oral orforglipron produced greater average weight reduction than placebo over 72 weeks with shared lifestyle support. Its most informative result combines meaningful average loss, varied responder outcomes, and measurable tolerability costs. Missing weights and discontinuation do not erase the finding, but they explain why the estimand and imputation method matter. The evidence supports this intervention within its studied population; it does not establish superiority over another oral drug, long-term cardiovascular benefit, post-withdrawal durability, or any provider's outcomes.
Sources & documentation
Scientific and official sources consulted October 21, 2026. Study findings apply to the populations, products and time periods described; they are not provider outcome data.
- Orforglipron, an Oral Small-Molecule GLP-1 Receptor Agonist for Obesity Treatment. ↗
- DailyMed - FOUNDAYO- orforglipron tablet, film coated ↗
- Oral Semaglutide at a Dose of 25 mg in Adults with Overweight or Obesity. ↗
- Tirzepatide as Compared with Semaglutide for the Treatment of Obesity. ↗
- FDA concerns with unapproved GLP-1 drugs used for weight loss ↗